Digital medication information assurance

The PRSB has published new guidance to define how medication dose and timings are communicated digitally between systems in all care settings.

Overview

When people move between different healthcare settings, it’s important that the information about their medications can be shared easily with all the professionals involved in their care. At the moment, hospital and primary care clinicians prescribe differently which means that details about medications and their use instructions vary between settings. The information has to be checked and sometimes translated manually by clinicians. This is time consuming and can lead to errors.

NHS Digital guidance sets out how to communicate medication dose and timings digitally between systems without any change or loss of accuracy or meaning. This will make it easier for patients and clinicians in different care settings to obtain, use and import to their own systems, a patient’s medications, helping them to provide the right care and improve medication safety for patients.

The supporting PRSB information includes a non-technical guidance document for health and care professionals and patients. PRSB standards have been updated to include this medications model.

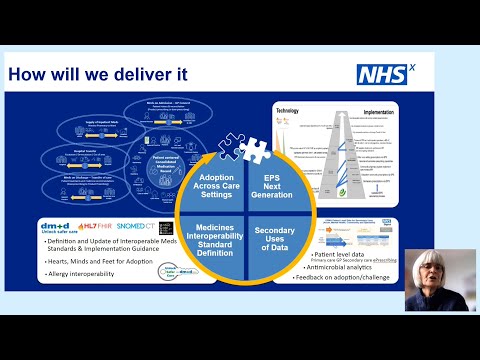
Ann Slee, Associate Chief Clinical Information Officer at NHS England talks to PRSB about the vision for medicines information sharing and how standards are critical to this work. Watch the video clips here.

Video Playlist
1/6 videos
1

Drivers for change
Drivers for change
2
The need for medicines interoperability
3

The overprescribing review
4
The vision and challenge
5
What has been implemented so far
6
Next steps
Next steps
Endorsement
  • Faculty of Clinical Informatics
  • Royal College of General Practitioners
  • Royal College of Physicians
  • Royal College of Nursing
  • Royal Pharmaceutical Society
  • Royal College of Emergency Medicine
  • Royal College of Anaesthetists
  • Royal College of Paediatrics and Child Health
  • Royal College of Obstetricians & Gynaecologists
  • Royal College of Psychiatrists
  • Royal College of Midwives
  • Royal College of Surgeons
  • Royal College of Occupational Therapists
  • Royal College of Ophthalmologists
  • Royal College of Speech & Language Therapists
  • College of Paramedics
  • British Association of Perinatal Medicine
  • British & Irish Orthoptic Society
  • Care Provider Alliance
  • Chartered Society of Physiotherapy
  • British Dietetic Association

IHRIM record correction guidance

Despite vigilance when filing information in records, mistakes can occur. The Institute of Health Records and Information Management has guidance to support professionals in making corrections following errors.

CHAT theory also explicitly addresses five areas which if addressed systematically will help overcome stakeholder differences in pursuit of the common goal:

1. Understanding the artefacts that characterise the group and its activity.
• The artefacts might be clinical settings or the forms and templates used to capture and share information. During the pilot we heard about hard copy Dialog response forms; locally generated templates for collating information from different systems; letters and emails to GPs; images, poems or other non-text artefacts that service users might want to include in their ‘about me’ or care plan.

2. Understanding the multi-views of the group. Such groups are always a community of multiple points of view, traditions and interests. 
• Different participants in the group will have different roles and will bring to the group and their roles their own histories, language, and ‘rules’. During our Stocktake preparations and workshops we worked with psychiatrists, mental health nurses, occupational therapists, social workers, transformation leads and voluntary sector representatives, all professions and interests with their own language, approaches professional ‘rules’ but united in their interest in care plans, care planning.

3. Activity systems (like the ICSs) take shape and get transformed over periods of time. ‘Historicity’ is a term coined to express how the group’s problems and potentials can only be understood against their own history. 


• ‘We’ve always done it this way’, ‘that didn’t work before’, ‘it’s always like this’, ‘it wasn’t always like this’, ‘they are changing things again’, are all typical statements that often frustrate those charged with overseeing change initiatives. Without addressing the experiences that lie behind such comments you risk repeating mistakes of the past, alienating your stakeholders or just not understanding the real starting point for your transformation project. This is particularly the case for the implementation of the PCSP standard, the success of which will be largely reliant on point-of-care practices and information protocols as well as having systems which are user friendly and appropriately configured.

4. The central role of contradictions as sources of change and development. Contradictions are not the same as problems or conflicts. Contradictions are historically accumulating structural tensions within and between activity systems. Collectively addressing contradictions in how policy, practice, culture and technology interact will empower teams to find genuinely novel solutions for apparently intractable challenges, like interoperability and shared care plan/planning. 

This links to the fifth principle that:

5. the possibility of expansive transformations in activity systems. As the contradictions of an activity system are aggravated, some individual participants begin to question and deviate from its established norms. In some cases, this escalates into collaborative envisioning and a deliberate collective change effort. “An expansive transformation is accomplished when the object and motive of the activity are re-conceptualised to embrace a radically wider horizon of possibilities than in the previous mode of the activity.”